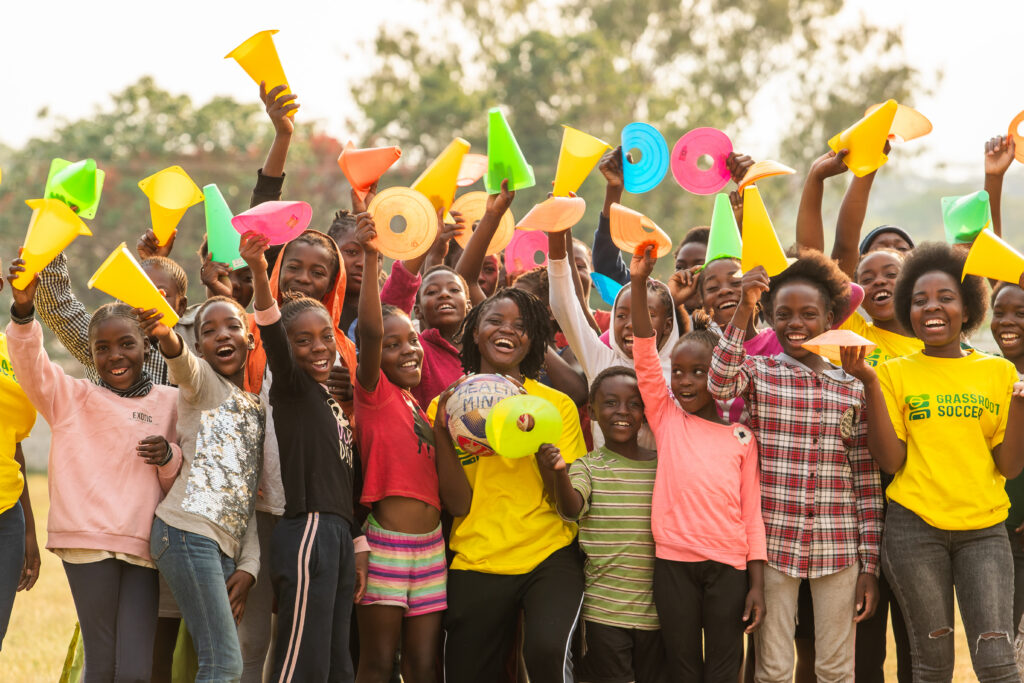Background and hypothesisPrevious studies have shown an association between social cognition (emotion recognition, social perception, attributional style, and mentalization) and post-traumatic stress disorder (PTSD), but there have been no longitudinal studies on this topic. We hypothesize that childhood social cognitive differences are associated with subsequent trauma exposure and PTSD.Study designData from the Longitudinal Study of Parents and Children (ALSPAC) were used. The Social Communications Disorder Checklist (SCDC) at age 7.5 years, the Diagnostic Analysis of Non-Verbal Accuracy Scale (DANVA) Receptive Facial Expressions Subtest at 8 years, and the Emotional Triangles task at 13.5 years were used. Outcome measures were trauma ages 14–23 years using the LEC-5 and screening positive for PTSD at 23 years of age using the PCL-5. Logistic regression analyses were used and adjusted for sex, socioeconomic status, verbal IQ, and autism diagnosis for the trauma outcome and, additionally, childhood trauma ages 0–10 years for the PTSD outcome. A sensitivity analysis examined whether an association remained with adolescent/adult trauma after excluding those with childhood trauma.Study resultsGlobal social cognition differences measured via the SCDC were associated with trauma in the main and sensitivity analyses (ORadj 1.09, 95% CI 1.08, 1.11, p-value <0.001) as were errors on the Triangles task (ORadj 1.04, 95% CI 1.03, 1.06, p-value <0.001). The SCDC was also associated with PTSD (ORadj 1.15, 95% CI 1.12, 1.18, p-value <0.001) as were errors on the Triangles task (ORadj 1.16, 95% CI 1.13, 1.20, p-value <0.001). No association was found with the DANVA task and the outcomes measured.ConclusionsThese results support a temporal relationship between social cognitive variation and subsequent trauma and PTSD.
People increasingly turn to conversational AI for companionship, emotional support, and well-being, using both purpose-built companion apps, such as Replika and Character.AI, and general-purpose assistants, such as ChatGPT and Claude. While some evidence suggests potential benefits, including short-term reductions in loneliness and mood improvement, several adverse outcomes have been reported in both clinical and nonclinical populations, including emotional dependence, exacerbation of symptoms, and self-harm. The fluent and apparently empathic responses from these models lead users to engage with them not only as tools but also as if they were social entities. This framing is conceptually misleading and may pose risks across different user profiles, particularly for vulnerable individuals. Drawing on research in AI, psychiatry, psychology, and network science, we highlight mechanisms through which emotional reliance develops and the boundary between tool and companion erodes. Design choices that evoke personality and warmth encourage users to anthropomorphize these systems. Simulated empathy, generated through probabilistic language patterns rather than genuine emotional experience, creates a structurally asymmetric interaction, in which the user discloses and the system responds, but without reciprocity, vulnerability, or accountability. Overvalidation and sycophancy can reinforce maladaptive cognitions, delusional ideation, and distorted perceptions of reality, as they tend to reinforce people’s beliefs, even at the expense of the accuracy of models’ responses. These mechanisms are not incidental: they emerge from alignment procedures that reward responses perceived as warm and empathic. The result is a self-reinforcing feedback loop between the model and the user that may amplify maladaptive beliefs, delusional ideation, and emotional distress, even in those who engage for largely functional purposes. Understanding these dynamics requires an examination of both what these agents can do—considering their technical limitations and implementations—and what humans believe they can do, including social and psychological impacts. We argue that conversational AI should be treated primarily as a tool supporting human systems rather than as a substitute for human relationships. Perhaps more importantly, reviewing the current hype surrounding AI interactions can help reformulate a paradigm that contributes to human well-being and societal value, while minimizing misconceptions, maladaptive interactions, or social disintegration.
<img src="https://jmir-production.s3.us-east-2.amazonaws.com/thumbs/31acb2c2de9a6960a54052d3939a044a" />
Neurodiversity-affirming mental health care requires not only adapting support to neurodivergent people but also examining the relational assumptions through which alliance, empathy, cooperation, progress, and risk are interpreted. This Conceptual Analysis develops the heuristic concept of relational-proximity priors: implicit assumptions that emotional closeness, rapid reciprocity, eye contact, visible warmth, and ready acceptance of help are generally reliable indicators of therapeutic fit or improvement. Drawing primarily on autism research and, more cautiously, on broader neurodivergence-informed literature, the paper synthesizes work on neurodiversity, double empathy, minority stress, healthcare accessibility, interpersonal distance, epistemic injustice, and psychotherapy process. The argument is that when such priors remain unaudited, clinically meaningful behaviors such as distance, reduced affect display, written communication, slower pacing, or literal style may be misread as resistance, poor alliance, or lack of insight. The paper further proposes that these priors can become sedimented in service routines, documentation practices, and AI-supported systems if observation and interpretation are not adequately separated. The article does not present a validated empirical construct or a systematic review; rather, it offers a theory-anchored conceptual synthesis and a set of heuristic audit tools intended to slow interpretation and widen clinically plausible hypotheses. Implications are discussed for psychotherapy, service design, documentation, participatory evaluation, and AI governance in public mental health.
Get your daily dose of health and medicine every weekday with STAT’s free newsletter Morning Rounds. Sign up here.
Good morning. I didn’t have space to mention it yesterday, but can you believe Nathan Fielder made an Elizabeth Holmes documentary? Variety called it shameless and fascinating. I may need to see for myself.
IntroductionIn mental health research involved with sensitive features and privacy issues, using integrated data offers an efficient alternative to traditional approaches such as interviews or in−person data collection. These conventional methods frequently face logistical barriers, including low response rates among study populations. Using integrated data from multiple existing administrative and survey sources provides protection for participants and economic savings for researchers, despite being constrained by the limitations of the original data sources. Our research questions were: 1) Can we conduct path and network analyses of school absenteeism, psychosocial factors, and mental health outcomes using the integrated survey data from New Zealand’s Integrated Data Infrastructure (IDI)? and 2) How can we account for the complex design of the General Social Survey (GSS) to ensure representative inference?Materials and methodsThe study population was New Zealand youth enrolled in school, aged 15 years and older in 2018, who participated in the 2018 GSS. The study analyzed the Ministry of Education data integrated with the 2018 GSS survey data from New Zealand’s IDI. To explore the relationship between outcomes of including the WHO-5, “perceived life worthwhileness”, “perceived general health”, and predictors including school absenteeism, psychosocial factors, and family factors, quantile mixed−effects regression, path analysis, and Bayesian network (BN) analysis were used. The complex survey design was calibrated using replicated weights from the GSS, a design-based method for complex sampling, in path and regression analyses, and bootstrap resampling, in BN analysis.ResultsIn descending order from the weighted path model, overall life satisfaction (standardized path coefficient: 0.36), perceived health condition (0.34), ease in accepting cultural identity (0.12), and trust in the education system (0.07) were all significantly (positively) related to students’ mental health well-being (WHO-5). Perceived life worthwhileness correlated with the WHO-5 but was only connected to overall life satisfaction. Similar factors were identified for perceived health, with additional attributing factors, such as fear of crime in the area and the family’s overall well-being.ConclusionThe integration of Bayesian networks and path analysis offers rigorous methods for detecting complex interrelationships among integrated mental health outcomes from population data and variables from a complex survey design.
IntroductionAutism Spectrum Disorder (ASD) screening requires multimodal biomarkers to capture the heterogeneous neurological and behavioral phenotypes. Current screening approaches remain siloed across EEG analysis and conversational assessment, limiting integrated diagnostic architecture. Privacy-preserving machine learning frameworks for mental health screening are underdeveloped, particularly for multilingual deployment contexts. This paper presents NeuroCon-AutismNet, a candidate multimodal architecture integrating diffusion-regularized EEG synthesis, multilingual conversational screening, and formal differential privacy as architectural proof-of-concept. No diagnostic discrimination capability is claimed; all validation is scoped to synthetic evaluation.MethodsNeuroCon-AutismNet comprises four modules: (1) Temporal Diffusion Biomarker Generator (TDBG), a latent diffusion model over VAE-encoded 19-channel EEG; (2) Multilingual Affective Dialogue Screening Network (MADSN), a fine-tuned GPT-2-small module deployed in English, Spanish, and Hindi; (3) Neuro-Linguistic Fusion Transformer (NLFT), enforcing positional alignment as a design prior rather than learned cross-modal association; and (4) Adaptive Mixture-of-Experts Layer (AMEL-X) for entropy-regularized multimodal fusion. Formal (ε, δ)-differential privacy (ε = 1.0, δ = 1e-5) is verified via DP-SGD RDP composition (σ = 1.2, q = 0.0914, T = 550 steps, verified ε = 0.97). Privacy verification establishes architectural readiness for future real-data deployment; no real patient records are present in the training set.Results and DiscussionWithin closed synthetic evaluation, held-out diagnostic AUC is 0.503 (95% CI: 0.487–0.519, DeLong p = 0.67), statistically indistinguishable from chance and the central limitation of this study. Two partial external benchmarks are provided. Spectral comparison against three independently published real ASD EEG studies yields Pearson r = 0.87 across five frequency bands; delta and alpha directions are reproduced, but theta and gamma reproduce poorly with large amplitude errors (delta MAE 14.79%, alpha MAE 11.57%). Expert evaluation of MADSN outputs by 50 annotators under single-blind protocol yields 90% empathy satisfaction and Cohen’s κ = 0.82, reflecting text quality rather than clinical screening validity. The null diagnostic AUC and synthetic-only evaluation prevent any current screening or clinical-utility claims. Real-data EEG validation, clinician-caregiver interaction studies for MADSN, and DP-protected training on real patient records are prerequisites for future clinical deployment.
Background: Empathic communication in the clinical setting has been associated with improved clinical outcomes, decreased anxiety, and increased patient satisfaction, treatment adherence, and trust. Despite the recent growth in patient portal use, the expression of empathic communication through patient portal secure messages is not well understood. Objective: This study aimed to construct a coding schema to define and assess empathic opportunities initiated by patients and primary care clinicians’ responses to these opportunities within a patient portal messaging environment. Methods: Data for this study included adult patient secure messages and responding messages from clinicians working in family practice clinics within a regional health care system serving central and northeast Pennsylvania between January 2018 and December 2023. We conducted a manual review of messages using the Empathic Communication Coding System as a guiding framework, which defines empathic opportunities created by patients and corresponding empathic responses by clinicians. We double-coded 500 patient messages for 3 empathic opportunity types: statements of emotion, progress, and challenge. Coding definitions were iteratively updated to describe specific textual cues unique to the patient portal context. This procedure was repeated to code for empathy in clinician responses to empathic opportunities. An additional 100 patient messages were double-coded for interrater reliability testing, and 500 patient messages were single-coded using the finalized coding schema. Results: Among 1100 patient messages coded, 576 (52.4%) included an empathic opportunity. Of these messages, 100 (17.3%) included a statement of emotion, 85 (14.7%) included a statement of progress, and 539 (93.6%) included a statement of challenge. Statements of challenge were primarily characterized by patients explicitly describing physical or mental health issues, a barrier in care, or difficulties in their personal lives. Among the 576 patient messages with empathic opportunities, 446 (77.4%) received at least 1 response from a clinician. Clinicians sent 483 response messages, of which 64 (13.2%) expressed empathy. Conclusions: While patients created empathic opportunities in over half of patient portal secure messages, primary care clinicians infrequently responded with empathy. The findings of this study provide initial evidence of gaps in empathic communication within patient portal secure messages and lay the groundwork for using artificial intelligence models to systematically measure and improve this communication across the patient portal messaging system.
<img src="https://jmir-production.s3.us-east-2.amazonaws.com/thumbs/b25d0804a4d183367c4b91a44f24e0f8" />
By Mai El Shoush, Partnership Campaign Manager, SNF Global Center for Child and Adolescent Mental Health at the Child Mind Institute
Few events unite the world quite like the FIFA World Cup, demonstrating soccer’s unique ability to connect people across cultures and communities. As millions tune in, the moment offers a timely reminder on how sports can reach young people far beyond the field. This belief underpins the work of Grassroot Soccer, a valued partner of the SNF Global Center for Child and Adolescent Mental Health at the Child Mind Institute. They utilize the power of soccer to advance youth mental health — and have reached more than 25 million young people around the world through this approach.
The partnership incorporates three interconnected areas:
Building capacity for frontline workers
Generating evidence
Contributing to thought leadership on child and adolescent mental health in low-resource settings
The 2026 Men’s World Cup in North America and the upcoming 2027 Women’s World Cup in Brazil present an important opportunity for the organization to take its mental health programming from sub-Saharan Africa and adapt it to the U.S. context.
We spoke with Grassroot Soccer’s Mental Health Specialist Charmaine Nyakonda about the organization’s approach, the impact of their collaboration with SNF, and the growing role of sports in improving the mental health of young people and communities globally.
Grassroot Soccer’s Mental Health Specialist, Charmaine Nyakonda
As international attention increasingly turns towards soccer’s global reach with the 2026 FIFA Men’s World Cup, what role can sports play in advancing youth mental health care across diverse communities?
Soccer is the most popular and accessible sport in the world. From the largest global stages like the World Cup to the most remote rural villages, it’s played everywhere on the planet. As the World Cup shows, soccer has the power to captivate across geographies, cultures, and time zones.
Soccer (and sport in general) is a powerful tool that teaches youth important life skills and character-building lessons like resiliency, hard work, courage, trust, and teamwork. On top of this, soccer’s universal appeal across diverse communities means using the language of the game can also be an effective way to break through the stigma around sensitive but pressing topics like mental health. This is why Grassroot Soccer uses soccer as a teaching tool for mental health.
Grassroot Soccer has successfully touched the lives of millions of young people across settings worldwide. What has the team learned about the universal role that sports can play in supporting mental health, resilience, and social connection?
Across our programs, soccer serves as a universal entry point that hooks young people and meets them where they are. From there, our play-based activities use soccer games and metaphors to make learning about mental health fun and engaging. They break down stigma and create safe spaces where young people can feel comfortable opening up and being vulnerable. This drives exceptional participation and completion rates.
Importantly, our signature soccer-based mental health promotion and prevention program, called MindSKILLZ, is guided by core mental health design principles. This includes grassroots co-creation, trauma-informed practice, relationship-centered delivery, and strengths-based learning — which ensures that programs are ethical, culturally grounded, and safe for adolescents in both stable and crisis-affected settings.
“Soccer (and sport in general) is a powerful tool that teaches youth important life skills and character-building lessons like resiliency, hard work, courage, trust, and teamwork.”
What elements of Grassroot Soccer’s approach do you believe could serve as a transferable blueprint for other organizations seeking to improve outcomes for young people in different sectors and communities?
Our commitment to co-design with young people: We believe that young people are the experts on their lives and needs, so we intentionally apply the principle of “Nothing about us without us” to our work. We put this into practice by engaging young people at every point in the program life cycle to ensure our work meets their needs, from design to implementation to evaluation.
In 2023, Grassroot Soccer officially launched a Youth Advisory Committee (YAC) composed of young leaders that serves as an internal advisory and advocacy body for the organization. The Committee consists of SKILLZ Coaches, Master Coaches, and trainers between the ages of 18 to 30 from the communities we serve.
Mental health integration: Mental health promotion and prevention must be woven into every service that young people access. Mental health is both a driver and an outcome of young people’s overall well-being. Unaddressed mental health challenges undermine progress in HIV, sexual and reproductive health, education, and other youth development areas. And those same factors profoundly shape young people’s mental health in return.
What has made the partnership with the SNF Global Center particularly valuable, and what role do cross-sector and multidisciplinary partnerships play in expanding support and opportunities for young people?
The diverse cultural perspectives from Greece, Brazil, the United States, and South Africa — and especially youth voices — have enriched our understanding of the barriers young people face, the values that motivate them, and the creative solutions they come up with when it comes to mental health.
We’ve also benefited tremendously from the scientific and clinical expertise at the SNF Global Center. We were able to co-develop an open-access, near-peer emotional support online training that aims to enhance the capacity of frontline workers to identify, refer, and support common mental health problems among children and adolescents. This is especially important in low-resource settings.
Additionally, through thought leadership and advocacy collaboration, this partnership has been valuable in contributing to an important shift in the global conversation to framing low-resource settings (the Global South) as sources of innovation that can positively impact the Global North.
Over the years, what has most reinforced your belief in the power of soccer to support youth mental health, and what examples best bring that impact to life?
We’ve seen a few powerful stories of impact in humanitarian settings, where the need for mental health care is at its greatest but resources are at its most limited.
For example, in 2024, relentless downpours following a tropical cyclone caused rivers in Malawi’s Nkhotakota and Karonga districts to overflow, leading to widespread flooding impacting over 150,000 people and forcing many displaced residents to seek refuge in makeshift internally displaced person (IDP) camps.
In the camps, people had no access to mental health and psychological support services or safe spaces, and youth were not attending school. The Malawi Ministry of Health identified a major gap in mental health support for adolescents and young people and called on Grassroot Soccer to deliver MindSKILLZ to respond to this need.
Grassroot Soccer’s response team focused heavily on play, coping skills development, and trauma-informed support, creating critical psychological and physical safe spaces for youth within the camp environment.
Looking ahead, how would you like to see the conversation evolve at the intersection of sports, youth well-being, and mental health?
Firstly, we would like to see the conversation move beyond asking whether adolescent girls and young women like to play sports and instead asking, “What can we unlock when they do?”
For too long, sports (and soccer in particular) have been understood as primarily a significant part of adolescent boys’ and young men’s lives only. That assumption has shaped who gets access, who feels welcome, and whose well-being is centered. Grassroot Soccer’s own programming challenges this directly — we have reached more adolescent girls than boys, and in doing so have created space for girls to reconstruct gendered ideas about soccer. The conversation on sports, youth, and mental health needs to evolve to view sports games like soccer as universal tools that can transcend gender norms, age, and socio-economic background to support young people.
At the same time, we want to see the conversation take adolescent boys’ mental health more seriously, not less. Qualitative insights from Grassroot Soccer show that rigid masculine norms remain a profound barrier for boys.
More broadly, we ultimately want to see the conversation shift from individual resilience to multi-systemic access and inclusive enabling environments. Young people need culturally grounded, safe environments that work for them — and include them in design and delivery to help them develop into healthy adults who carry that capacity forward.
What do you see as the greatest opportunities for the next generation of young people, and what must we do collectively to help make that future possible?
With the largest generation of adolescents coming of age, their ability to live healthy and productive lives will have a profound impact on not just their own life trajectories, but also on the world. Tackling critical global issues from poverty to climate change will require a generation of young people who are strong, healthy, and empowered — and their mental health is central to all this.
At Grassroot Soccer, we are committed to investing in youth mental health to realize a world where mental health challenges have been normalized. We want young people to understand their own mental health, have practical coping skills to deal with frustration and aggression, and recognize the value in seeking support from others. This will help develop a population with reduced symptoms of depression and anxiety, as well as overall improved mental well-being. Then we can collectively realize our vision for a better future.
Through the SNF Global Center, the Child Mind Institute partners with organizations around the world to strengthen child and adolescent mental health systems by combining scientific expertise, local leadership, evidence-based innovation and youth voices. Grassroot Soccer is one example of how cross-sector partnerships can expand access to mental health support in communities where young people already learn, connect, and thrive.