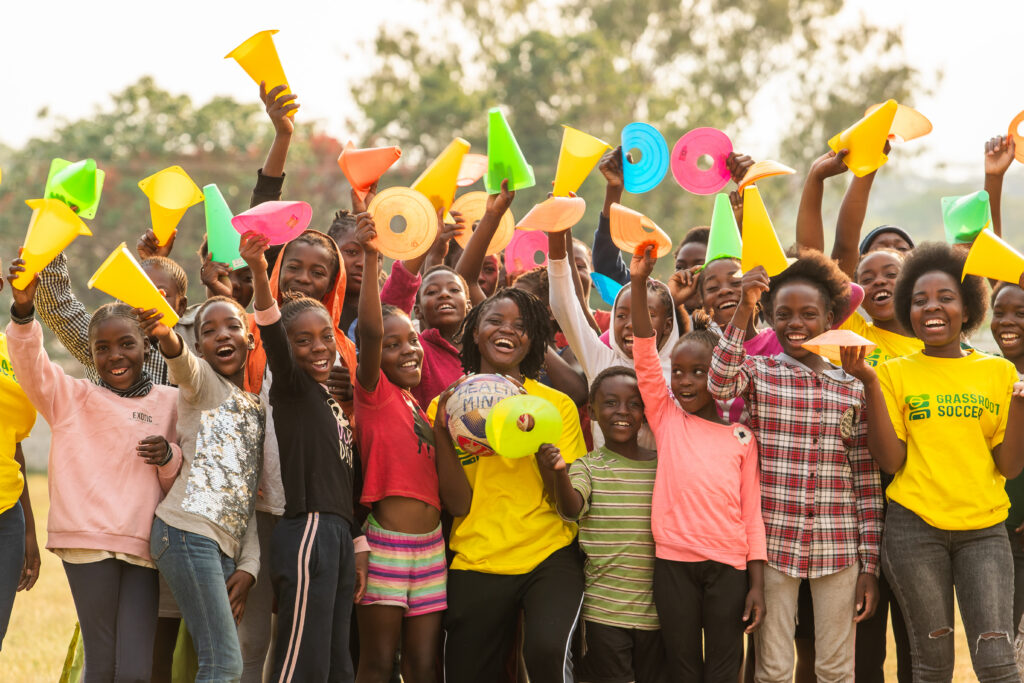Background: Social media is an increasingly prominent channel for communicating menopause information and experiences, yet the affective and behavioral consequences of different narrative framings remain unclear. Objective: We examined how distress, normalizing, and transformative narratives influenced women’s immediate responses to menopause content online, drawing on established narrative framings of menopause as normality, distress, and transformation. Methods: In an online experiment, UK women aged 40 to 83 years who were perimenopausal or postmenopausal were recruited via Prolific, a widely used online recruitment platform for behavioral and social science research. A total of 737 women were randomly assigned to view 4 anonymized and standardized social media posts from a pool of 12 reflecting 1 of 3 narratives: <i>normal</i> (n=248, 33.6%), <i>distress</i> (n=241, 32.7%), or <i>transformative</i> (n=248, 33.6%). Participants then reported affective reactions, expected behavioral responses, and perceptions of the posts using 5-point ordered response scales. Ordinal logistic regression models tested demographic predictors and condition effects controlling for demographic factors. Results: Participants who viewed distress-framed posts reported greater levels of worry (β=.910; <i>P</i><.001), confusion (β=.818; <i>P</i><.001), and anxiety (β=.817; <i>P</i><.001) and lower levels of reassurance (β=−.970; <i>P</i><.001), optimism (β=−.708; <i>P</i><.001), and empowerment (β=−.540; <i>P</i><.001). Distress framing also increased perceived knowledge of menopause (β=.564; <i>P</i><.001) despite participants feeling more negatively toward the posts. Neither distress nor transformative narratives influenced expected behavioral intentions to like, share, save, comment on, search for, or discuss social media posts compared with normalizing narratives. Postmenopausal status (β=−.630; <i>P</i><.001) and older age (β=−.492; <i>P</i><.001) were independently associated with less worry and anxiety. Participants rated distress (β=−.806; <i>P</i><.001) and transformative posts (β=−.968; <i>P</i><.001) as less representative of health professionals than normalizing posts; transformative posts were also judged to be less representative of newspapers or television (β=−.687; <i>P</i><.001). Conclusions: Narrative framing shaped immediate affect but not intended engagement with menopause content. Because this study assessed short-term responses to controlled, standardized posts, future research should examine whether these effects persist over time and how they operate in more ecologically valid social media environments. As public discussion expands, diverse, balanced narratives may help reduce stigma and temper the disproportionate salience of negative framing. This study advances understanding of how narrative framing shapes responses to health content online.
By Mai El Shoush, Partnership Campaign Manager, SNF Global Center for Child and Adolescent Mental Health at the Child Mind Institute
Few events unite the world quite like the FIFA World Cup, demonstrating soccer’s unique ability to connect people across cultures and communities. As millions tune in, the moment offers a timely reminder on how sports can reach young people far beyond the field. This belief underpins the work of Grassroot Soccer, a valued partner of the SNF Global Center for Child and Adolescent Mental Health at the Child Mind Institute. They utilize the power of soccer to advance youth mental health — and have reached more than 25 million young people around the world through this approach.
The partnership incorporates three interconnected areas:
Building capacity for frontline workers
Generating evidence
Contributing to thought leadership on child and adolescent mental health in low-resource settings
The 2026 Men’s World Cup in North America and the upcoming 2027 Women’s World Cup in Brazil present an important opportunity for the organization to take its mental health programming from sub-Saharan Africa and adapt it to the U.S. context.
We spoke with Grassroot Soccer’s Mental Health Specialist Charmaine Nyakonda about the organization’s approach, the impact of their collaboration with SNF, and the growing role of sports in improving the mental health of young people and communities globally.
Grassroot Soccer’s Mental Health Specialist, Charmaine Nyakonda
As international attention increasingly turns towards soccer’s global reach with the 2026 FIFA Men’s World Cup, what role can sports play in advancing youth mental health care across diverse communities?
Soccer is the most popular and accessible sport in the world. From the largest global stages like the World Cup to the most remote rural villages, it’s played everywhere on the planet. As the World Cup shows, soccer has the power to captivate across geographies, cultures, and time zones.
Soccer (and sport in general) is a powerful tool that teaches youth important life skills and character-building lessons like resiliency, hard work, courage, trust, and teamwork. On top of this, soccer’s universal appeal across diverse communities means using the language of the game can also be an effective way to break through the stigma around sensitive but pressing topics like mental health. This is why Grassroot Soccer uses soccer as a teaching tool for mental health.
Grassroot Soccer has successfully touched the lives of millions of young people across settings worldwide. What has the team learned about the universal role that sports can play in supporting mental health, resilience, and social connection?
Across our programs, soccer serves as a universal entry point that hooks young people and meets them where they are. From there, our play-based activities use soccer games and metaphors to make learning about mental health fun and engaging. They break down stigma and create safe spaces where young people can feel comfortable opening up and being vulnerable. This drives exceptional participation and completion rates.
Importantly, our signature soccer-based mental health promotion and prevention program, called MindSKILLZ, is guided by core mental health design principles. This includes grassroots co-creation, trauma-informed practice, relationship-centered delivery, and strengths-based learning — which ensures that programs are ethical, culturally grounded, and safe for adolescents in both stable and crisis-affected settings.
“Soccer (and sport in general) is a powerful tool that teaches youth important life skills and character-building lessons like resiliency, hard work, courage, trust, and teamwork.”
What elements of Grassroot Soccer’s approach do you believe could serve as a transferable blueprint for other organizations seeking to improve outcomes for young people in different sectors and communities?
Our commitment to co-design with young people: We believe that young people are the experts on their lives and needs, so we intentionally apply the principle of “Nothing about us without us” to our work. We put this into practice by engaging young people at every point in the program life cycle to ensure our work meets their needs, from design to implementation to evaluation.
In 2023, Grassroot Soccer officially launched a Youth Advisory Committee (YAC) composed of young leaders that serves as an internal advisory and advocacy body for the organization. The Committee consists of SKILLZ Coaches, Master Coaches, and trainers between the ages of 18 to 30 from the communities we serve.
Mental health integration: Mental health promotion and prevention must be woven into every service that young people access. Mental health is both a driver and an outcome of young people’s overall well-being. Unaddressed mental health challenges undermine progress in HIV, sexual and reproductive health, education, and other youth development areas. And those same factors profoundly shape young people’s mental health in return.
What has made the partnership with the SNF Global Center particularly valuable, and what role do cross-sector and multidisciplinary partnerships play in expanding support and opportunities for young people?
The diverse cultural perspectives from Greece, Brazil, the United States, and South Africa — and especially youth voices — have enriched our understanding of the barriers young people face, the values that motivate them, and the creative solutions they come up with when it comes to mental health.
We’ve also benefited tremendously from the scientific and clinical expertise at the SNF Global Center. We were able to co-develop an open-access, near-peer emotional support online training that aims to enhance the capacity of frontline workers to identify, refer, and support common mental health problems among children and adolescents. This is especially important in low-resource settings.
Additionally, through thought leadership and advocacy collaboration, this partnership has been valuable in contributing to an important shift in the global conversation to framing low-resource settings (the Global South) as sources of innovation that can positively impact the Global North.
Over the years, what has most reinforced your belief in the power of soccer to support youth mental health, and what examples best bring that impact to life?
We’ve seen a few powerful stories of impact in humanitarian settings, where the need for mental health care is at its greatest but resources are at its most limited.
For example, in 2024, relentless downpours following a tropical cyclone caused rivers in Malawi’s Nkhotakota and Karonga districts to overflow, leading to widespread flooding impacting over 150,000 people and forcing many displaced residents to seek refuge in makeshift internally displaced person (IDP) camps.
In the camps, people had no access to mental health and psychological support services or safe spaces, and youth were not attending school. The Malawi Ministry of Health identified a major gap in mental health support for adolescents and young people and called on Grassroot Soccer to deliver MindSKILLZ to respond to this need.
Grassroot Soccer’s response team focused heavily on play, coping skills development, and trauma-informed support, creating critical psychological and physical safe spaces for youth within the camp environment.
Looking ahead, how would you like to see the conversation evolve at the intersection of sports, youth well-being, and mental health?
Firstly, we would like to see the conversation move beyond asking whether adolescent girls and young women like to play sports and instead asking, “What can we unlock when they do?”
For too long, sports (and soccer in particular) have been understood as primarily a significant part of adolescent boys’ and young men’s lives only. That assumption has shaped who gets access, who feels welcome, and whose well-being is centered. Grassroot Soccer’s own programming challenges this directly — we have reached more adolescent girls than boys, and in doing so have created space for girls to reconstruct gendered ideas about soccer. The conversation on sports, youth, and mental health needs to evolve to view sports games like soccer as universal tools that can transcend gender norms, age, and socio-economic background to support young people.
At the same time, we want to see the conversation take adolescent boys’ mental health more seriously, not less. Qualitative insights from Grassroot Soccer show that rigid masculine norms remain a profound barrier for boys.
More broadly, we ultimately want to see the conversation shift from individual resilience to multi-systemic access and inclusive enabling environments. Young people need culturally grounded, safe environments that work for them — and include them in design and delivery to help them develop into healthy adults who carry that capacity forward.
What do you see as the greatest opportunities for the next generation of young people, and what must we do collectively to help make that future possible?
With the largest generation of adolescents coming of age, their ability to live healthy and productive lives will have a profound impact on not just their own life trajectories, but also on the world. Tackling critical global issues from poverty to climate change will require a generation of young people who are strong, healthy, and empowered — and their mental health is central to all this.
At Grassroot Soccer, we are committed to investing in youth mental health to realize a world where mental health challenges have been normalized. We want young people to understand their own mental health, have practical coping skills to deal with frustration and aggression, and recognize the value in seeking support from others. This will help develop a population with reduced symptoms of depression and anxiety, as well as overall improved mental well-being. Then we can collectively realize our vision for a better future.
Through the SNF Global Center, the Child Mind Institute partners with organizations around the world to strengthen child and adolescent mental health systems by combining scientific expertise, local leadership, evidence-based innovation and youth voices. Grassroot Soccer is one example of how cross-sector partnerships can expand access to mental health support in communities where young people already learn, connect, and thrive.
BackgroundPerimenopausal women frequently experience physiological and psychological symptoms, including anxiety, depression, and panic disorders, mainly due to declining ovarian function and hormonal changes. Current options include pharmacotherapy, acupoint stimulation (AcuStim), and psychotherapy (psych), but their comparative efficacy and safety remain controversial.ObjectiveThis network meta-analysis (NMA) systematically compared pharmacotherapy, AcuStim, and psychotherapy for perimenopausal anxiety, depression, and panic disorder, assessing clinical efficacy, adverse events (AEs), and changes in the Hamilton Depression Rating Scale (HAMD), Hamilton Anxiety Rating Scale (HAMA), Kupperman Index (KI), Self-rating Depression Scale (SDS), Self-rating Anxiety Scale (SAS), Pittsburgh Sleep Quality Index (PSQI), and serum hormone levels.MethodsWe searched PubMed, Embase, Cochrane Library, Web of Science, CNKI, Wanfang, VIP, and SinoMed from inception to June 14, 2026, for randomized controlled trials (RCTs). A Bayesian NMA was performed, and the Surface Under the Cumulative Ranking Curve (SUCRA) was calculated.ResultsThe study included 131 RCTs, encompassing 11457 perimenopausal women diagnosed with emotional disorders. These trials evaluated three distinct treatment strategies. The NMA showed that the highest SUCRA probabilities were observed for drug_psych across HAMD (SUCRA = 92.4%), KI (SUCRA = 97.9%), SDS (SUCRA = 94.5%), PSQI (SUCRA = 98.1%), and follicle-stimulating hormone (FSH) (SUCRA = 96.1%) reduction and estradiol (E2) (SUCRA = 0.1%) elevation; for AcuStim_psych (SUCRA = 93.7%) in HAMA reduction; for psych (SUCRA = 98.9%) in SAS reduction; for drug_AcuStim in clinical efficacy (SUCRA = 9.0%) and luteinizing hormone (LH) reduction (SUCRA = 100%); and for control (SUCRA = 65.5%) in safety outcomes. In pharmacotherapy subgroup analyses, antidepressants (ADs)_Traditional Chinese medicine (TCM) ranked highest for HAMD (SUCRA = 87.2%) and safety (SUCRA = 82%), ADs_antipsychotics (AP) (SUCRA = 97.5%) for HAMA, and ADs_hormone replacement therapy (HRT) (SUCRA = 10.2%) for clinical efficacy.ConclusionPharmacological, acupoint stimulation, and psychological interventions each demonstrated therapeutic benefits for perimenopausal women with emotional disorders. Combination therapies generally showed more favorable efficacy across multiple psychological and endocrine outcomes than single-modality interventions, while no single treatment strategy was consistently superior across all outcomes. These findings may provide evidence to support individualized treatment selection according to patients’ clinical characteristics and therapeutic goals.Systematic review registrationhttps://www.crd.york.ac.uk/PROSPERO/, identifier CRD420261340530.
BackgroundChinese healthcare professionals face dual pressures from clinical duties and research activities, which may increase research-related anxiety and reduce job satisfaction. While occupational stress has been well studied, the mechanisms linking research stress to job satisfaction are unclear. Research performance may also play a key role, but its impact remains uncertain. This study explores the relationships between research stress, research anxiety, research performance, and job satisfaction, and identifies the pathways connecting these variables.MethodsA cross-sectional survey was conducted among healthcare professionals (nurses, physicians, and pharmacists) from eastern, central, and western regions of China to assess research-related conditions and job satisfaction (JS). Job satisfaction was measured using a modified validated scale. Research stress (RS), research anxiety (RA), and research performance (RP) were assessed using self-developed instruments. Structural equation modeling (SEM) was employed to perform path analysis and mediation analysis.ResultsA total of 924 healthcare professionals were included in the study. Over 85% reported working more than 40 hours per week, and 66.5% rated their health status as fair or poor. Regarding the types of research conducted by healthcare professionals, clinical research accounted for the highest proportion (63.2%), followed by basic science research (9.8%), while health services research and community-based research were relatively less common. The mean scores of JS, RS, RA, and RP were 3.40 ± 0.88, 2.56 ± 0.70, 2.34 ± 0.87, and 3.55 ± 0.82, respectively. Path analysis revealed that research stress was positively associated with research anxiety and negatively associated with both research performance and job satisfaction. Research anxiety was also negatively associated with research performance and job satisfaction, whereas research performance was positively associated with job satisfaction. Mediation analysis indicated that research stress was associated with job satisfaction both directly and indirectly through research anxiety and research performance.ConclusionsResearch stress is negatively associated with job satisfaction among healthcare professionals through increased research anxiety, whereas higher research performance is positively associated with job satisfaction. Hospitals and healthcare institutions should optimize the research environment, strengthen psychological support, and enhance research resource allocation to reduce research stress, improve research performance, and ultimately increase job satisfaction.
Categorical nosological systems frequently fall short when confronted with patients whose presentations cross established diagnostic boundaries. We report M.S., a 44-year-old Brazilian man involuntarily admitted to a psychiatric inpatient unit who presented with systematized persecutory ideation of mechanistic–technological content (chip implantation, satellite-based surveillance), structural ego fragility, absent insight, and progressive social and occupational deterioration. While prior diagnoses of bipolar disorder and provisional schizophrenia had been considered, neither fully captured the clinical complexity. Psychopathological-dimensional analysis, grounded in phenomenological observation and contemporary psychopathological theory, suggests three potentially interacting axes: (1) structural ego fragility (Ich-Schwäche), potentially arising from impaired early attachment and deficient relational learning; (2) a relational causality deficit replaced by concrete–mechanistic reasoning; and (3) limbic hyperactivation that appears to sustain an anxiety–perplexity–paranoia feedback loop. These converge on a schizotypal–affective spectrum formulation. Laboratory investigations identified severe dyslipidemia and marked hyperandrogenism (total testosterone 1,367 ng/dL), the latter potentially associated with limbic hyperactivation, though causality cannot be established from a single cross-sectional measurement. Psychometric assessment (BPRS-18) at admission yielded a total score of 43, with suspiciousness (5) and unusual thought content (5) as dominant items. During a seven-day inpatient course, a multimodal thymic strategy—risperidone, lithium carbonate, and structured psychotherapy—produced attenuation of paranoid reactivity, improved family engagement, and the spontaneous resumption of guitar playing from day 3, as a functional correlate of behavioral stabilization. The patient was discharged with a referral for a three-monthly paliperidone palmitate long-acting injectable. The pharmacological response retrospectively supports the dimensional formulation and illustrates the heuristic value of psychopathological analysis grounded in ego structure, causal reasoning, and affective dysregulation as a complementary approach to categorical nosology in complex psychotic–affective presentations.
BackgroundAcademic burnout is a mental-health-relevant outcome of higher-education stress, but its relationship with spontaneous brain dynamics remains unclear. EEG microstates are quasi-stable scalp-potential configurations indexing millisecond-level transitions between large-scale resting brain states. This study tested whether resting-state EEG microstate dynamics are associated with academic burnout beyond trait anxiety, depressive symptoms, and general self-efficacy as perceived coping capacity.MethodsParticipants were 330 Chinese undergraduates (94 men, 236 women; mean age = 18.31 years, SD = 0.84). They completed self-report measures and an eyes-closed resting-state EEG recording. Academic burnout total score was the primary outcome. Covariate-adjusted partial correlations examined burnout–microstate associations. Hierarchical regression tested the incremental value of selected microstate markers.ResultsHigher academic burnout was associated with higher trait anxiety (r = 0.539, p < 0.001), higher depressive symptoms (r = 0.526, p < 0.001), and lower general self-efficacy (r = -0.474, p < 0.001). After adjustment for age, sex, trait anxiety, depressive symptoms, and general self-efficacy, greater burnout was associated with shorter microstate D duration (partial r = -0.196, q = 0.0049), higher microstate C occurrence (partial r = 0.172, q = 0.0081), shorter mean microstate duration, and higher mean occurrence. The psychological block explained substantial variance in burnout (R² = 0.417); adding microstate D duration and microstate C occurrence produced a small but significant improvement in model fit (ΔR² = 0.025, p = 0.001). In a scale-midpoint sensitivity analysis, the higher-burnout group showed shorter class D duration after covariate adjustment (adjusted B = -3.38 ms, 95% CI [-6.12, -0.64], p = 0.016). Dimension-specific analyses indicated that microstate associations were mainly evident for dejection and low sense of accomplishment, not the behavioral (improper-behavior) component.ConclusionAcademic burnout in undergraduates was primarily linked to internalizing distress and lower perceived coping capacity. Resting-state EEG microstate dynamics, especially shorter class D duration, provided modest incremental information, suggesting reduced temporal persistence of a canonical resting-state configuration among students with higher burnout. These findings do not establish a diagnostic EEG marker or a burnout-specific neural mechanism, but support multimodal, context-sensitive research on academic stress and mental health in higher education.
Background: Mobile mindfulness interventions have shown promise for reducing anxiety and depressive symptoms, but sustaining engagement remains a persistent challenge. Many digital programs still rely on formal practice that requires dedicated time, which may be difficult to integrate into daily life. Objective: This randomized controlled trial evaluated Habitual Mindfulness Practice (HMP), a self-guided mobile mindfulness intervention that embeds brief practices into recurring daily routines, among adults with mild to moderate psychological distress. Outcomes were compared with those of Traditional Mindfulness (TM), Mindfulness-Based Psychoeducation (MBP), and a waitlist control (WL). Methods: Adults aged 18 to 65 years with mild to moderate symptoms of anxiety or depression were randomly assigned in a 1:1:1:1 ratio to HMP, TM, MBP, or WL (N=686). All procedures were conducted online, and the intervention was fully self-guided, with outcomes assessed using self-report measures. The intervention lasted 21 days, with assessments conducted at baseline, postintervention, and 3-month follow-up. Primary outcomes were depressive and anxiety symptoms. Secondary outcomes included mindfulness, cognitive emotion regulation, affective balance, and interpersonal difficulties. Postintervention group differences were examined, controlling for baseline scores, and longitudinal trajectories were evaluated across the active intervention conditions. Results: At postintervention, significant group effects were observed for depressive symptoms (=28.67, <.001, ηp²=0.11) and anxiety symptoms (=30.11, <.001, ηp²=0.12). Both HMP and TM showed lower depressive and anxiety symptom scores than MBP and WL. TM showed lower postintervention anxiety than HMP (=.04), whereas depressive symptoms did not differ significantly between HMP and TM (=.63). The mindfulness practice conditions also showed more favorable postintervention outcomes for mindfulness, affective balance, interpersonal difficulties, and emotion regulation. Improvements in depressive and anxiety symptoms were generally maintained at follow-up among the active intervention conditions, although maintenance of secondary outcomes varied across measures. Postintervention outcome data were available for 55.2% (379/686) of randomized participants, and follow-up outcome data were available for 24.1% (124/515) of participants in the active intervention conditions. HMP and TM did not differ significantly in practice duration, engagement, or satisfaction. Conclusions: A routine-embedded, self-guided mobile mindfulness intervention may be a feasible approach for reducing mild to moderate psychological distress. HMP produced benefits broadly comparable to those of traditional app-delivered mindfulness, but it did not confer advantages in engagement or short-term efficacy. Trial Registration: Chinese Clinical Trial Registry ChiCTR2400093771; https://tinyurl.com/3d6tky8v
Background: The postpartum period represents a critical window for maternal health, yet many individuals lack sustained support and timely identification of physical and mental health risks. Digital health interventions offer a scalable approach to extend care beyond clinical settings. Yet, key elements, including real-world challenges, usability, and effectiveness of such platforms, are insufficiently characterized in this literature. Objective: This study aimed to conduct a formative randomized evaluation to assess the feasibility, engagement, and preliminary signals of impact of the Joyuus platform and to examine the potential for early identification of postpartum health risks. Methods: We conducted a 12-week randomized evaluation with postpartum participants recruited through community-based organizations. Participants were randomized to either the Joyuus intervention or standard postpartum care. Primary and secondary outcomes included the Barkin Index of Maternal Functioning, the Edinburgh Postnatal Depression Scale (EPDS), the State-Trait Anxiety Inventory, and the Connor-Davidson Resilience Scale. Analyses were conducted using an intention-to-treat approach with linear regression models adjusting for baseline values. Engagement metrics (ie, sessions, time on site, and feature use) were captured through in-app analytics. An exploratory predictive model was developed using baseline clinical, behavioral, and demographic variables to identify individuals at risk for postpartum depression. Results: Baseline characteristics were generally balanced across arms, and no statistically significant differences were observed in education, income, or marital status. No statistically significant differences were found between treatment and control groups in the 12-week changes for the primary or secondary outcomes. Mean EPDS scores were 9.7 in the intervention group and 9.3 in the control group. In the sample, 60 (45.5%) of the 132 participants met the criteria for elevated depression (EPDS score ≥11 or a positive response to question 10 on self-harm), indicating a high burden of symptoms within the study population. Engagement with the platform was highest during the first 4 weeks. Among intervention participants, 80% created an account. Participants reported high levels of perceived usefulness, ease of use, and relevance of content. Qualitative analysis of open-ended survey responses highlighted limited awareness of postpartum-specific resources and a preference for simple, accessible information. An exploratory predictive model demonstrated a recall of 0.89 and a precision of 0.73 in identifying individuals at risk for postpartum depression, suggesting the feasibility of early risk identification using integrated data inputs. Conclusions: Joyuus demonstrated feasibility and acceptability but did not produce statistically significant improvements in maternal functioning or maternal health outcomes over 12 weeks. Joyuus identified high rates of depressive symptoms and early engagement patterns, which suggest an opportunity for earlier identification of risk and intervention during the postpartum period. Exploratory modeling results indicate the potential for data-driven approaches to support earlier detection. Future work includes optimizing engagement strategies and expanding validation of predictive detection to improve postpartum surveillance and outcomes. Trial Registration: ClinicalTrials.gov NCT05876559; https://clinicaltrials.gov/study/NCT05876559?cond=postpartum%20joyuus&viewType=Card&rank=1
This blog was originally posted by the TLC Foundation for BFRBs
Body-focused repetitive behaviors (BFRBs) and obsessive-compulsive disorder (OCD) are two distinct mental health conditions that share some similarities but also have significant differences. BFRBs involve repetitive, self-grooming behaviors that can cause physical damage, such as hair pulling or skin picking. On the other hand, OCD is a condition characterized by intrusive thoughts (obsessions) and repetitive behaviors (compulsions) performed to alleviate anxiety.
While both conditions involve repetitive behaviors and can impact daily life, their underlying mechanisms, triggers, and treatment approaches differ. This article explores the key similarities and differences between BFRBs and OCD to better understand these complex conditions.
Similarities Between BFRBs and OCD
Most professionals view BFRBs and OCD as similar conditions due to the similarity in symptoms, such as compulsivity and repetitive behaviors. These two conditions share several similar systems and are usually a reaction to triggering factors such as stress and anxiety. Below are some of their similarities.
Repetitive Behaviors
Individuals dealing with BFRBs often engage in various repetitive behaviors such as hair pulling, lip biting, or skin picking. These actions are usually challenging to control and are frequently triggered by stress or anxiety. One may indulge in the habit subconsciously to find instant relief from the trigger.
Individuals with OCD often experience intrusive thoughts that result in repetitive behaviors known as compulsions. Some common compulsions include washing hands and repetitively checking or counting to alleviate the stress caused by obsessive thoughts. In both conditions, the repetitive behaviors are often exacerbated by stress and anxiety, and individuals may adapt these behaviors as a coping mechanism.
Impulse Control
Closely related to repetitive behaviors is the concept of impulse control. Both BFRBs and OCD involve challenges in this area, albeit in different ways. Individuals with BFRBs and OCD may find it hard to control the urge to perform repetitive behaviors. This is because these repetitive behaviors often relieve tension. Despite knowing the consequences of these behaviors, the desire to indulge in them is usually irresistible.
For example, individuals with BFRBs understand that hair pulling may affect their appearance, but they cannot refrain from doing it. OCD occurs as a result of intrusive thoughts whereby one believes that if they do not perform a specific action, the stressor won’t go away. These intrusive thoughts often cause anxiety, which can be eased by engaging in the said repetitive behavior.
Onset and Course
Having examined the behavioral aspects, let’s now consider how these conditions develop over time. The onset of these two conditions shares several similarities regarding age, triggers, and psychological mechanisms.
The onset of both conditions is usually during childhood or adolescence and often coincides with various developmental changes and stressors. For individuals with BFRBs, the repetitive behaviors alleviate stress and anxiety instantly. At the same time, for those with OCD, performing the compulsions temporarily relieves them from the stress caused by their intrusive thoughts. The cognitive patterns involve repetitive actions, intrusive thoughts, and a lack of impulse control. In BFRBs, the urge to engage in these repetitive behaviors can be intrusive and persistent, while in OCD, one’s obsessions create a sense of urgency, which leads to the adoption of compulsive actions.
Neurobiological Factors
To fully understand the similarities between BFRBs and OCD, we must delve deeper into their biological underpinnings. Both conditions have a genetic origin and are associated with neurobiological factors. Neurobiological studies indicate that the impulse control and emotional regulation difficulties for people with BFRBs and OCD are often caused by abnormalities in brain regions that are responsible for impulse control and habit formation. Therefore, the underlying brain mechanism may result in the onset and development of both conditions. It is not uncommon for individuals to have both BFRBs and OCD or for both conditions to coincide with other mental health conditions, usually depression and anxiety. The overlap is generally because they typically share common underlying factors that play a part in their severity and development.
Differences Between OCD and BFRBs
While BFRBs and OCD share several commonalities, it’s equally important to understand their distinct characteristics, from the symptoms to the underlying mechanisms. Let’s explore the key differences that distinguish these two conditions.
Nature of the Behavior
First and foremost, let’s examine how the behaviors associated with each condition differ in their fundamental nature. Individuals dealing with these two conditions adopt diverse behaviors as coping mechanisms for their triggers. In BFRBs, the behaviors adopted, such as trichotillomania (hair-pulling) or cheek-biting, usually result in physical harm. However, regardless of the consequences, one always feels relieved when picking their skin or pulling their hair.
OCD, on the other hand, involves a wide range of compulsions, from washing to organizing, checking, and counting. Compulsive behaviors are performed due to intrusive thoughts that make one think that if they fail to indulge in a specific behavior, they might get hurt, or there might be other negative consequences.
Presence of Obsessions
Another crucial distinction lies in the cognitive processes behind these behaviors. Generally, BFRBs do not involve obsessive thoughts. The primary focus on BFRBs is usually more on the physical behavior and not the fear of specific consequences.
However, the major characteristic of OCD is intrusive thoughts, which increase the urge to indulge in particular behaviors for relief. The thoughts are usually persistent with unwanted images that result in distress.
People with BFRBs DO NOT report that if they do not pick on their skin, something terrible will happen. Instead, they report that picking or pulling their hair helps relieve them from intense and negative emotions. These behaviors, therefore, serve a self-regulatory function, unlike in OCD, where the repetitive behavior calms them from their intrusive thoughts.
Triggers
The nature of triggers for each condition is closely related to the presence or absence of obsessions. The primary trigger in BFRBs is stress and anxiety, but for OCD, the main trigger is intrusive thoughts, which then result in anxiety. OCD and BFRBs triggers differ in several ways, often resulting in different outcomes. OCD triggers often result in one taking measures to prevent harm, while for BFRBs, one uses the adopted behaviors to regulate and manage intense emotions. The nature of thoughts is an essential distinguishing factor, seeing as OCD involves intrusive and obsessive thoughts that trigger specific behaviors adopted to prevent harm. The purpose of compulsions in OCD is to reduce the anxiety caused by the obsessive thoughts, while in BFRBs, the behaviors are for emotional relief.
Awareness
Beyond triggers, the level of conscious awareness also differentiates these two conditions. Those dealing with BFRBs usually find themselves biting their nails or even pulling their hair subconsciously. Individuals with OCD are generally aware of their intrusive thoughts and are compelled to adopt specific behaviors as a response to these thoughts. Individuals with OCD are often aware of their compulsions and understand when they are being irrational, but they are unable to control themselves. Compared to people with OCD, those with BFRBs often find their behaviors more rewarding than distressing.
Treatment
Finally, while both conditions may benefit from cognitive behavioral therapy, the specific approach to treatment varies significantly. For individuals with BFRBs, the focus is on behavior modification and awareness, achieved through habit reversal training. For OCD, the emphasis is often placed on exposure to anxiety-provoking thoughts to help an individual tolerate anxiety, which prevents compulsive behavior.
Bottom Line
While BFRBs and OCD can coexist, they are distinct disorders with unique manifestations despite sharing some similarities. The key distinctions between these conditions are evident in their underlying mechanisms and treatment approaches.
Both involve compulsive behaviors, but their purposes differ. BFRBs primarily serve as subconscious tools for emotional regulation. OCD compulsions are conscious attempts to alleviate anxiety and prevent perceived harmful consequences. BFRB behaviors often occur with limited conscious awareness, while OCD sufferers are typically more aware of their compulsive actions.
Both conditions can significantly affect daily functioning and social interactions.BFRBs may lead to physical injuries and lowered self-esteem due to visible effects. OCD can cause severe anxiety and time-consuming rituals that interfere with daily activities.BFRB treatment emphasizes behavior modification and awareness techniques, while OCD treatment often involves exposure therapy to reduce anxiety responses.
Understanding these distinctions is crucial for accurate diagnosis and effective treatment. While both conditions present challenges, with proper support and intervention, individuals with BFRBs or OCD can learn to manage their symptoms and improve their overall quality of life.